
I am introducing my spine surgical decision-making app, which guides you through a thoughtful process for deciding whether to undergo spine surgery. It is intended for both patients and clinicians. Most surgeons are well-intentioned, but modern medicine has compromised our capacity to listen and get to know you. This process will help you fully engage in your final decision, which may be one of the most important of your life. It is available at: drdavidhanscom.com.

My background
Many of you are aware that I performed complex spine surgery for 32 years. I was one of the surgeons in Seattle who treated many patients with failed back surgeries. There is even a name for it: Failed Back Surgery Syndrome (FBSS).
From 1990 to 2003, I endured severe, chronic mental and physical pain. I had no idea what was happening or how to escape. No one seemed able to help me. From the day I slipped into this Abyss, I embarked on a relentless search for answers. There was a lot of trial and error, mostly error. But I kept pursuing answers. When I came out of the Abyss in 2003, I still didn’t understand the why or how. However, my 17 symptoms resolved and stayed gone for over 20 years.
I eventually figured it out and learned to share healing concepts with my patients through a process that empowered them to take charge of their care. It was largely self-directed, using my books and website as resources. My contribution was minimal, but I provided a safe foundation and background. I did not have much time to talk with my patients amid a busy full-time practice. I learned that patients must take control of their care and their lives, and without that engagement, I could not offer much.
Surgery is rarely a definitive solution, and effective alternatives exist.
I began to witness hundreds of patients not only break free from pain but also thrive at levels they had never experienced. At the same time, I saw three to five patients every week who had failed back surgery, often with devastating outcomes. It was unbelievable how bad it could get. Most of these failures began with surgery on normally aging spines, which have been documented not to be a source of chronic pain. Many surgeons and patients view surgery as the definitive answer. It is not. Surgery only works for a specific symptom caused by a specific anatomical problem. The data also shows that even a clearly indicated operation performed in the presence of untreated chronic pain can worsen the pain 40-60% of the time for up to a year and is permanent in 10%. This statistic is not widely known.
The decision-making process
In 2006, I presented a talk on surgical decision-making. It turns out there are only two variables to consider.
- Is there a structural abnormality that correlates with the symptoms?
- Is the nervous system sensitized or calm?
This decision-making grid evolved into the basis of my book, Do You Really Need Spine Surgery? It is not about avoiding necessary surgery but about optimizing your outcome, with or without it. The goal is to help you heal, with or without surgery.
Making the correct decision about spine surgery
The decision to undergo spinal surgery is not as difficult as you might think. You only need to consider two factors. One is the anatomy, and the other is the state of your nervous system.
Is there a clearly identifiable source of your pain causing symptoms that correspond to it? Or is it arising from irritation of tissues that cannot be seen on an imaging study?
The second factor is the state of your nervous system. If you have been feeling stressed for more than three months, your body’s chemistry is on “high alert,” which affects every cell in your body, including nerve conduction speed and your brain’s inflammatory state. (1) You will not only experience more pain; your capacity to cope with it is compromised.
Another issue when you feel trapped is that your brain activity shifts from the neocortex (thinking region) to the brain’s lower parts (survival). As a result, you cannot think clearly, and by definition, your decision-making will be flawed. You are not going to be thinking about philosophy while you are running from the lion.
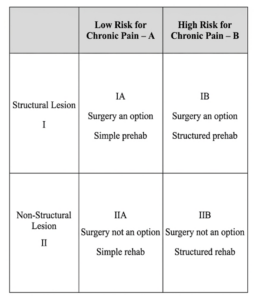
With these two variables of the anatomy and state of your nervous system, there are four scenarios to consider:
- IA—Structural lesion, low risk for chronic pain
- IB—Structural lesion, at risk for chronic pain (high stress)
- IIA—Non-structural lesion, low risk for chronic pain
- IIB—Non-structural lesion, at risk for chronic pain (high stress)
An overview of how this looks is presented in this grid:
This app is designed to be used and referenced over several months as you make your decision. The process helps you understand the issues and small details you must address. You might feel you don’t want to spend the time to engage, and sometimes a quick decision works. However, you don’t want to be one of the failures, and you can’t comprehend the havoc caused by unindicated surgery. Don’t cut corners.
One reason surgeons perform surgery is that we believe that if patients have come to us, they have failed non-operative care and nothing else can be done. But non-operative care isn’t structured or defined. Viable options exist; they are effective, carry minimal risk, and require minimal resources.
What resources do I have to optimize your care?
- Your Healing Companion – com – surgical navigation app
- The DOC Journey course – a self-directed, computer-based course to calm and reroute your nervous system.
- Books
Whether you access my resources or another’s based on similar principles, please deeply understand the nature of chronic pain and where surgery fits. Get it right the first time!